
Leadership in Biotech

Tag: diagnostic reasoning

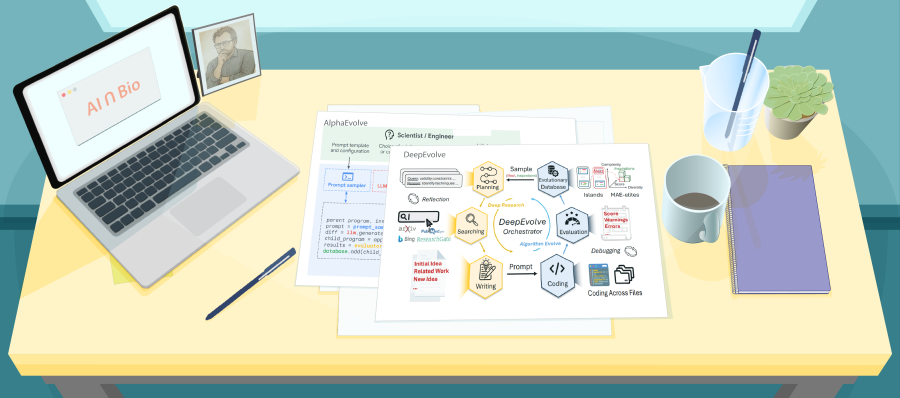
Illustration of a desk with figures from recent papers about DeepEvolve and AlphaEvolve

From AlphaEvolve to DeepEvolve: What We’re Learning About Machine-Led Scientific Discovery

Over the past year, AlphaEvolve (DeepMind) and DeepEvolve (Liu et al.) have taken on one of science’s most audacious challenges: can machines not only execute discovery but originate it? Both leverage large language models (LLMs) to iteratively evolve algorithms through feedback and automated evaluation.

AlphaEvolve reframed discovery as code evolution: LLMs proposing edits, testing them, and optimizing against performance scores. DeepEvolve extends this paradigm by integrating deep research: literature retrieval, structured reasoning, multi-file implementation, and automatic debugging. Together, they signal a shift from code-writing tools to more active scientific collaborators and raise foundational questions about what counts as “understanding.”

Scientific Insight

AlphaEvolve’s achievements are real and impressive: it discovered a novel algorithm for 4×4 matrix multiplication, improving on a benchmark that had stood since 1969. But its limitations are equally instructive. When optimization is tethered entirely to scalar reward signals, models risk learning how to perform rather than how to understand.

DeepEvolve addresses some of this by incorporating retrieval-augmented reasoning and grounded iteration, showing measurable gains across nine domains—from molecular property prediction to polymer engineering. Yet the deeper challenge persists: these systems can refine heuristics, but they cannot yet articulate principles; the boundary between discovery and reward chasing remains unresolved.

Leadership Angle

For R&D leaders in life sciences or diagnostics, these systems are both technical achievements and strategic case studies.

Peter Drucker once warned: “What gets measured gets managed—even when it’s pointless to measure or manage it.” In the context of these papers, the risk is clear: if we measure only performance, we may optimize into blind alleys. The opportunity lies in designing systems (and organizations!) that ask better questions, not just produce better scores.

Mentorship Angle

For early-career scientists, the message isn’t to fear or avoid these tools (please don’t, these tools are amazing!), but to understand their limitations. AlphaEvolve and DeepEvolve can automate exploration, but perhaps not judgment. They can generate thousands of hypotheses in hours, but still depend on human insight to distinguish signal from noise. And require careful thought in setting up reward systems that uncover real meaning in the context you care about.

In a world where even machines can “research,” the defining trait of good science will be the discipline to ask whether improvement is meaningful, not just measurable. That’s the work of real discovery and no algorithm can evolve that for us (at least not yet!).

Illustration of a desk with a figure from a recent paper about diagnostic reasoning

What happens when physicians use GPT-4 for diagnosis

A randomized clinical trial in JAMA Network Open tested whether giving physicians access to GPT-4 improves diagnostic reasoning on challenging clinical vignettes. Fifty internists, family physicians, and emergency physicians were randomized to use either conventional tools (UpToDate, Google) or those tools plus GPT-4 for one hour of structured case work.

Result: having GPT-4 on hand did not significantly raise physicians’ diagnostic-reasoning scores—a blinded rubric capturing how well they generated and evaluated differentials, supporting and opposing evidence, and next steps. By contrast, GPT-4 alone, when run with a carefully standardized and pilot-tested prompt, outperformed both groups.

That detail matters: the model excelled under disciplined prompting, but real clinicians weren’t given that scaffolding. The study’s signal isn’t “AI beats doctors,” but that design and interaction quality determine whether large language models truly augment performance.

Scientific Insight

The primary outcome (structured-reflection score, a composite measure of diagnostic reasoning) was similar between groups: median 76% (GPT-4) vs 74% (control), adjusted difference +2 points (95% CI −4 to +8; P =.60). Time per case was also similar (−82 s; 95% CI −195 to +31). GPT-4 alone, using the fixed prompt, scored +16 points higher than control (95% CI 2–30; P =.03). Reliability was strong (weighted κ = 0.66; Cronbach’s α = 0.64).

The authors suggest that prompt quality and minimal user training explain the gap: the LLM performed best when given a carefully engineered, fixed prompt, but clinicians using it ad hoc gained little.

To ensure validity, cases came from a non-public vignette set edited to remove telltale phrases, and mixed-effects models accounted for case and participant clustering.

Leadership Angle

Signal to diagnostics leaders: Access ≠ adoption, adoption ≠ impact.

To lift reasoning quality, tools need workflow-aware design: standardized prompts, built-in reflection scaffolds, and short training, rather than open-ended chat.

The result of “GPT-4 > human doctors” here reflects a lab-grade setup, not real-world autonomy: vignettes lack interviewing, data gathering, and patient context. The next step is prospective workflow trials tied to diagnostic accuracy, testing, and safety outcomes.

Mentorship Angle

For early-career scientists and clinicians, this study itself teaches how to study AI well.

  1. Measure the reasoning, not just the answer. Chen et al. built a structured-reflection rubric that rewarded how clinicians weighed evidence for and against differentials—a model for rigorous evaluation design.
  2. Define and pre-register the human–AI handshake. Their fixed zero-shot prompt and blinded grading expose how interface and prompt choices shape performance; future work should test scaffolded vs free chat explicitly.
  3. Protect external validity. Using non-public vignettes and removing giveaway cues safeguarded against model leakage—a standard every diagnostic-AI study should meet.

This paper shows how careful experimental design lets us see what LLMs can really add to human reasoning (and workflows).

Powered by WordPress & Theme by Anders Norén